


Healthcare security teams don’t need another generic HIPAA checklist. They need proof. In 2025, healthcare data breaches exposed 168 million patient records, and the average cost of a single healthcare breach reached $10.93 million, the highest of any sector for the 14th consecutive year, according to Medha Cloud’s healthcare breach analysis.
That data changes the framing. HIPAA compliance requirements aren’t just legal obligations for privacy officers. They’re engineering requirements for identity, logging, encryption, monitoring, retention, and response. If your team can’t show how controls operate continuously, you may have policy language but not a defensible security program.
Most organizations already understand the theory. The harder problem is operationalizing it across endpoints, cloud apps, firewalls, identity providers, EHR systems, file shares, and vendor access. That’s where compliance efforts often stall. For a broader healthcare governance view, Simbie AI’s guide to compliance is a useful companion resource alongside the technical implementation work discussed here.
The High Stakes of HIPAA Compliance in 2026
Healthcare organizations live in a harsh asymmetry. One exposed mailbox, one over-permissioned contractor account, or one unmonitored export path can create a breach event that turns into regulatory review, legal expense, patient notification, and months of remediation work. HIPAA compliance requirements matter because healthcare systems hold data that attackers can monetize and patients can’t easily replace.
The bigger mistake is treating HIPAA as a policy binder problem. It isn’t. HIPAA is a control design problem. Security leaders have to prove that access is restricted, activity is logged, sensitive data is protected in transit and at rest, and suspicious behavior is investigated before a human reviewer asks for screenshots and reports.
Why the stakes are operational, not just legal
When compliance programs fail, they usually fail in the operating layer. The policy says access is role-based, but the directory still contains stale accounts. The standard says logs are reviewed, but the logs are split across appliances and cloud consoles. The incident plan exists, but the business associate never signed terms that align reporting duties across the chain.
Practical rule: If a control can’t generate evidence on demand, it’s not mature enough for healthcare.
That is why strong HIPAA programs look like security architecture, not paperwork. They define owners for logs, encryption, account lifecycle, vendor oversight, and incident response. They also reduce the gap between a compliance statement and the telemetry needed to prove it.
What security teams need instead of a checklist
A workable program usually includes three traits:
- Continuous visibility: Teams need unified telemetry from endpoints, network controls, identity systems, cloud platforms, and applications that handle ePHI.
- Control-to-evidence mapping: Each requirement should map to an artifact such as a log, alert, access review, change record, or signed agreement.
- Automated monitoring: Alerting for failed logins, unusual exports, privilege changes, and anomalous access has to run continuously, not only before an audit.
That’s the practical lens for the rest of this guide. HIPAA compliance requirements become manageable when each rule is translated into technical controls and auditable evidence.
Deconstructing the Four Core HIPAA Rules
HIPAA has four core rules, and each one creates technical work that can be monitored, tested, and proven. Teams that treat them as separate legal documents usually miss the operational point. The rules overlap in access design, logging, vendor control, incident handling, and evidence collection.
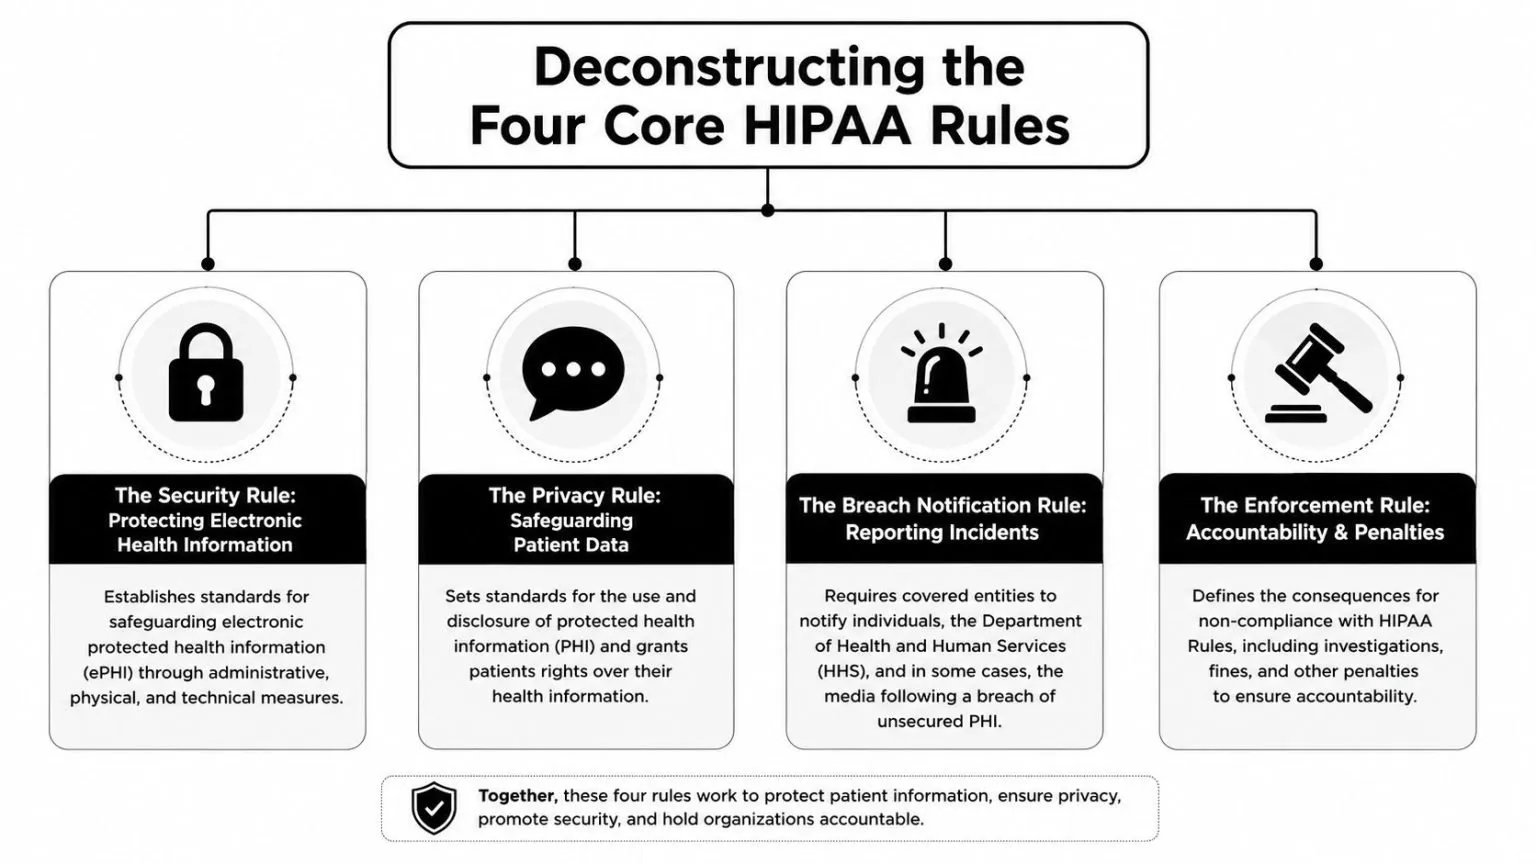
The Privacy Rule defines how PHI may be used and disclosed. For security and engineering teams, that shows up in minimum necessary access, application workflow boundaries, data retention choices, and whether a dataset should be identifiable at all. Privacy is not only a policy issue. It shapes permissions, data models, and what should or should not appear in logs, exports, and analytics pipelines.
The Security Rule applies those expectations to ePHI and turns them into safeguard requirements. Architectural design becomes paramount, encompassing identity controls, audit logs, encryption, endpoint telemetry, configuration baselines, and alerting. A unified SIEM and XDR platform such as UTMStack helps by centralizing the evidence trail, correlating access and security events, and keeping control validation continuous instead of episodic.
The Breach Notification Rule governs what happens after an impermissible disclosure or confirmed compromise of unsecured PHI. That requirement is often misunderstood as a legal deadline problem. It is also a telemetry problem. If teams cannot reconstruct who accessed what, from where, on which device, and whether data left the environment, they cannot scope the incident with confidence or defend their reporting decision.
The Omnibus Rule and enforcement framework extends those obligations to business associates and their subcontractors. Outsourcing a workload does not outsource accountability. If a billing vendor, SaaS provider, call center, or managed service provider handles PHI, their access paths, logging coverage, and incident reporting terms need to hold up under audit and during a real event.
For organizations reducing exposure at the design stage, methods for de-identifying healthcare data can lower both privacy risk and breach impact when applied correctly.
Why technical teams need all four in scope
Security teams often center their program on the Security Rule and leave the rest to legal or compliance. That split creates predictable failure points.
- Privacy decisions shape access control. If a department collects more data than its workflow requires, IAM and application permissions usually expand with it.
- Breach response depends on retained evidence. Notification decisions require log integrity, user context, asset context, and enough retention to reconstruct the timeline.
- Vendor governance needs technical controls. A signed BAA is only part of the answer. You still need scoped accounts, MFA, session visibility, alerting, and fast revocation.
- Enforcement risk rises when records do not match reality. Policies may say one thing while endpoints, cloud tenants, and third-party integrations show another.
The practical takeaway is simple. HIPAA works as one operating model. Privacy sets boundaries. Security implements controls. Breach notification tests whether monitoring and response are good enough. The enforcement layer asks for proof.
That is why mature programs map each rule to artifacts a platform can produce on demand, such as access logs, alert histories, configuration records, investigation notes, and vendor activity trails. A modern SIEM/XDR stack does not replace governance, but it gives compliance teams something auditors and incident responders both trust.
The Three Pillars of the HIPAA Security Rule
The Security Rule stands on three safeguard categories: Administrative, Physical, and Technical. Teams often over-rotate toward the technical side because it’s easier to buy tools than fix governance. In practice, the three pillars reinforce each other. Weak risk analysis undermines good logging. Weak facility controls undermine strong application controls.
HIPAA’s technical safeguards specifically mandate Access Control, Audit Controls, Integrity, Person or Entity Authentication, and Transmission Security, including implementation specifications such as unique user IDs and encryption aligned with NIST standards like AES-256, as outlined in this HIPAA software development guide.
Administrative safeguards
Administrative safeguards are the management layer. They decide who owns the program, how risk is assessed, how access is approved, how incidents are escalated, and how workforce members are trained.
In real environments, teams define:
- Risk analysis cadence: Annual assessment is the floor, not the whole program.
- Access governance: Joiner, mover, leaver processes need to align with clinical and vendor workflows.
- Security operations procedures: Alerts need triage logic, escalation paths, and response playbooks.
Physical safeguards
Physical safeguards are often underestimated because they feel old-school. They still matter. A badge-controlled server room, secure workstation placement, controlled device disposal, and media handling procedures remain part of the trust boundary around ePHI.
These controls become more relevant in hybrid care settings where clinicians, contractors, and support staff move between offices, clinics, and remote environments. A locked rack isn’t enough if laptops, removable media, and shared workstations are left outside policy.
Technical safeguards
Technical safeguards are the most visible and the most measurable. They are also the easiest to audit badly if controls exist without evidence.
| Safeguard Type | Objective | Example Implementation Specifications |
|---|---|---|
| Administrative | Govern how security is planned, assigned, and maintained | Risk analysis, workforce training, incident procedures, access approval workflows |
| Physical | Protect facilities, devices, and media that store or access ePHI | Controlled facility access, workstation controls, device disposal procedures |
| Technical | Enforce digital protection and accountability for ePHI | Unique user IDs, audit controls, authentication, integrity controls, encryption using AES-256 |
The strongest programs don’t implement these as separate workstreams. They tie them together. For example, an identity control isn’t just a login requirement. It connects policy, HR workflow, MFA settings, privileged access, endpoint telemetry, and alert review.
A HIPAA control is only complete when the organization can show who owns it, how it runs, and what evidence it produces.
That’s the difference between nominal compliance and defensible compliance.
Common Gaps and Costly Compliance Failures
The biggest HIPAA mistake isn’t malicious behavior. It’s assuming that documented intent is enough. OCR investigations repeatedly show that the dangerous failures are operational, recurring, and preventable.
The clearest example is risk analysis. The failure to perform the annual security risk analysis required by the Security Rule remains the most frequently cited failure in OCR investigations, which led to the launch of a specific Risk Analysis Initiative in October 2024 targeting non-compliant entities, according to Gitnux’s HIPAA statistics summary.

The paperwork myth
Organizations often say they completed a risk assessment when what they really completed was a questionnaire. That’s not the same thing. A true risk analysis traces where ePHI exists, how it moves, who can access it, which systems expose it, what logs exist, and which controls are missing or inconsistent.
A spreadsheet can document findings. It can’t discover unknown assets, stale permissions, weak log coverage, or insecure data paths on its own.
Where teams usually break down
The recurring weak points tend to look familiar:
- Identity drift: Accounts outlive job changes, vendor engagements, and temporary projects.
- Fragmented logging: EHR access logs, firewall logs, endpoint events, and cloud audit trails sit in different places.
- Weak BAA operations: Contracts exist, but onboarding and offboarding don’t enforce least privilege or monitoring.
- Shallow breach analysis: Teams treat every incident as either obviously reportable or obviously harmless without documenting the technical reasoning.
One nuanced area gets mishandled often. The distinction between a reportable breach and a low-probability compromise requires a documented technical risk assessment. Smith Law’s HIPAA analysis highlights how that documented analysis can become decisive during enforcement review.
Security teams get into trouble when they can describe a control in a meeting but can’t reconstruct the event trail that proves it worked.
The practical lesson is simple. HIPAA compliance requirements fail where monitoring, ownership, and documentation are weakest.
Implementing Technical Safeguards A Practical Blueprint
Technical safeguards work when they are specific, instrumented, and assigned to system owners. Broad security statements don’t help much. Engineers need to know which events to log, which sessions to terminate, which cryptographic standards to enforce, and how long artifacts must remain available.

Start with evidence-producing controls
Audit logging is mandatory. HIPAA logging must capture four immutable data points for every ePHI interaction: user identity, timestamp, action performed, and source location, and the logs need tamper protection with a minimum 6-year retention policy, as detailed in this developer-focused HIPAA checklist.
That requirement immediately translates into technical tasks:
- Who: Tie actions to unique user identities, not shared accounts.
- When: Preserve trustworthy timestamps across systems.
- What: Record read, write, delete, and export activity where the platform supports it.
- From where: Capture device or session origin so investigators can distinguish expected access from suspicious access.
For integrity monitoring, teams also need mechanisms that show when protected files, configurations, or binaries changed. A focused control such as file integrity monitoring for regulated environments helps close the gap between general logging and provable change tracking.
Map each safeguard to a system owner
The second mistake is implementing controls without ownership. HIPAA’s technical requirements usually span multiple teams, so each control needs an accountable operator.
Consider the core areas:
- Access control: Unique user IDs, emergency access procedures, automatic session controls, and permission review processes belong across IAM, EHR administration, and endpoint management.
- Integrity: Hash validation, change monitoring, and tamper detection belong to system administrators, application owners, and SOC analysts.
- Transmission security: Data in transit should use TLS 1.2 or TLS 1.3, while data at rest should use AES-256 with key management handled through validated cryptographic modules, based on the implementation guidance summarized earlier.
Critical vulnerabilities in systems containing ePHI also need fast remediation, and annual penetration testing plus continuous vulnerability scanning should be built into the operating rhythm rather than handled as occasional audit prep. The same applies to BAAs. They must be executed before a vendor accesses PHI, and the reporting obligation has to fit the incident response workflow, not sit only in legal storage.
Automating Compliance with a Unified SIEM and XDR
Manual HIPAA operations break down for a simple reason. The controls live everywhere. Identity data sits in one system. Endpoint telemetry sits in another. Firewall events, SaaS audit logs, vulnerability findings, and EHR activity all arrive in different formats and on different schedules. Reviewing them one by one doesn’t create continuous monitoring. It creates blind intervals.
Manual compliance doesn’t scale
Healthcare environments have a strong human factor. 68% of healthcare breaches stem from human error or inadequate access controls, and smaller practices often struggle to implement instant alerting and anomaly detection the Security Rule expects because they lack the tools, according to Rectangle Health’s HIPAA checklist discussion.
That is exactly where SIEM and XDR matter. A unified platform can:
- Ingest evidence broadly: Pull logs from cloud services, endpoints, network devices, identity providers, and applications that touch ePHI.
- Correlate behavior: Connect failed logins, privilege changes, unusual exports, remote access, and malware or endpoint events into a single investigation trail.
- Map detections to compliance controls: Associate alerts and reports with the safeguard they support.
- Retain evidence centrally: Preserve searchability for investigations, audits, and breach analysis.
One practical example is HIPAA compliance automation workflows, which align monitoring and reporting with control requirements instead of leaving teams to build every rule and evidence trail from scratch.
What a unified platform should actually do
A lot of vendors say they support HIPAA. The better question is whether the platform helps your team prove HIPAA compliance requirements continuously.
In practice, a unified SIEM/XDR should support at least four operating functions:
- Centralized audit collection for authentication events, admin actions, file access, endpoint detections, and network activity.
- Correlation rules for suspicious combinations such as repeated failed access followed by a successful login and large data movement.
- Alert workflows that assign incidents, preserve analyst notes, and show what remediation occurred.
- Compliance reporting that exports evidence by control, system, timeframe, or incident.
A platform such as UTMStack fits this model by unifying SIEM, XDR, automated response, and compliance mapping in one stack. The important point isn’t the product category label. It’s whether your team can move from fragmented console reviews to one defensible evidence stream.
A quick product walkthrough helps make that concrete:

Good automation doesn’t replace judgment. It removes the repetitive evidence gathering that keeps analysts from doing judgment well.
That distinction matters in healthcare. The platform should accelerate reviewers, not hide the reasoning they need during an investigation or audit.
Building Your Audit-Ready Evidence Locker
Audit readiness is mostly about retrieval. Many organizations have some of the right controls, but they can’t assemble the evidence quickly enough, or they discover too late that one team kept logs, another team kept policies, and no one kept the decision trail tying them together.
What auditors usually want to see
A reliable evidence locker usually contains:
- Risk analysis artifacts: The current assessment, remediation decisions, and records showing follow-up.
- Access evidence: User provisioning records, role reviews, privileged access approvals, and access logs.
- Monitoring evidence: Alert history, investigations, tuning records, and documented reviews of system activity.
- Vendor documentation: BAAs, security review records, and proof of access boundaries for third parties.
- Training and policy records: Workforce acknowledgment and current approved procedures.
How to keep evidence ready all year
The strongest pattern is centralization. When logs, alerts, investigations, and reports are collected into one search layer, audit prep becomes a reporting exercise instead of a scavenger hunt. That’s why centralized log management for compliance operations matters so much in healthcare environments.
Build the evidence locker around recurring exports and preserved context. Keep reports tied to controls, preserve timestamps, store investigation notes with the related alert, and retain documentation that explains why an incident was classified the way it was. That last point matters for breach analysis and for defending low-probability compromise conclusions.
If your team can answer three questions quickly, you’re in good shape: what happened, who had access, and what proof shows the control operated as designed.
If you’re evaluating how to turn HIPAA compliance requirements into continuous technical evidence, UTMStack is worth a look as part of that process. It gives security teams a way to centralize logs, correlate activity, automate detection, and produce compliance-focused reporting without treating HIPAA as a once-a-year documentation exercise.


